+86 13638632902
 Jason@cleanroomequips.com


 MENU

In order to handle nosocomial infections, action is required in the area of negative-pressure isolation units through a comprehensive program involving the following components: airborne precautions, appropriate rooming of patients, validated differential pressure, functioning ventilation, use of appropriate criteria for selecting personal protective equipment (PPE), hand hygiene, disinfection of the environment, and staff training. Use of negative pressure makes it possible to prevent the release of contaminated air but is not able to substitute for standard infection control measures. This artICle describes the basic organizational and technical measures offered to healthcare institutions in order to minimize the risk of transmission.
Introduction
Negative pressure wards provide optimal conditions for isolating infectious sources and blocking airborne diseases. These specialized facilities minimize the spread of infectious diseases, protect healthcare workers from infection, and effectively prevent cross-infection between patients.
Key Benefits
- Containment of airborne pathogens
- Protection of medical staff
- Prevention of cross-infection
- Safe environment for high-risk procedures
Primary Applications
- Respiratory disease isolation
- Pandemic response units
- Emergency treatment of unknown pathogens
- High-risk procedure environments
What is a Negative Pressure Isolation Ward?
Negative pressure isolation wards are specialized Hospital rooms designed to isolate patients with infectious diseases transmitted through the air. They utilize directional airflow to ensure air moves from clean areas to contaminated areas, with lower static air pressure than surrounding spaces to prevent pathogen spread.
Design Principle
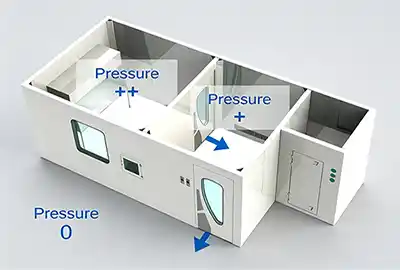
Air flows directionally from clean areas → semi-contaminated areas → contaminated areas
Ward pressure maintained lower than surrounding areas
air changes: 8-12 times per hour
Applications
- Pneumonic plague
- SARS and COVID-19
- Tuberculosis
- Measles
- Influenza
- Unknown pathogen emergencies

Design & Layout Requirements
Location Requirements
- Minimum 20m distance from other buildings
- Independent setup or at building ends
- Positioned downwind of prevailing winds
- Top floor preferred in high-rise buildings
Zone Requirements
- Strict separation: clean, semi-contaminated, contaminated areas
- Buffer zones between areas
- Dual corridors: inner (staff), outer (patient)
- Independent entrances/exits
Facility Requirements
Hand-washing Stations
With non-touch faucets
Shower Facilities
For decontamination
Double-door Pass-through
For safe transfer of items
Access Control
Prevent unauthorized entry

HVAC System Requirements
System Design
- Independent systems for eACH functional zone
- Fresh air mode or fan coil + fresh air
- No shared central AC with other wards
- Constant air volume system (24/7 operation)
Filtration Requirements
- Low-resistance high-efficiency filters
- Air quality: ≤500cfu/m³ bacteria
- Exhaust: ≥99.99% efficiency filters
- Filter replacement schedule critical
Air Handling Specifications
| Parameter | Requirement | Notes |
|---|---|---|
| air changes | 8-12 times/hour | Ward area |
| Fresh Air Volume | ≥40m³/h per person | Minimum requirement |
| Exhaust Speed | ≤1.5m/s | At return outlets |
| Fresh Air Intake | ≥3m above ground | ≥1m above roof |

Pressure & Airflow Management
Pressure Gradient
Clean area > Semi-contaminated > Contaminated
Clean area: Positive pressure
Semi-contaminated: Transition
Contaminated: Negative pressure
Minimum pressure difference: ≥5Pa between zones
Airflow Design
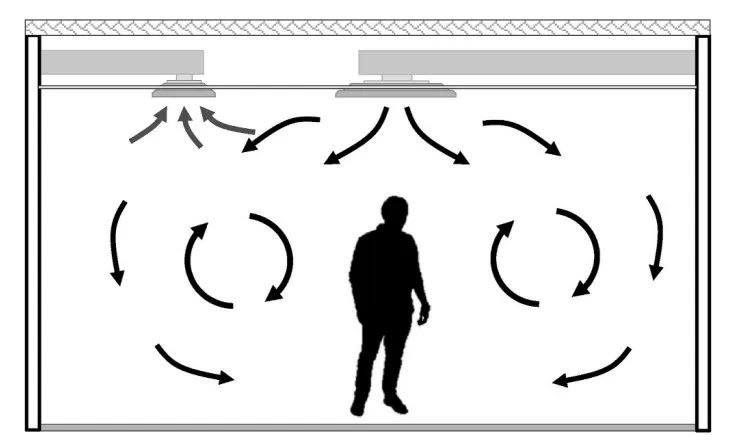
- Upper supply, lower side return
- Directional flow: clean → contaminated
- Main supply near staff position
- Exhaust near patient bed
- Avoid airflow between patient beds
Operational Guidelines
Staff Procedures
- Verify negative pressure before entry
- Wear appropriate PPE:
- Secondary protection: masks, gowns, gloves
- Tertiary for aerosol procedures: respirators
- Use hand-washing stations before/after
- Avoid standing near exhaust vents
Filter Maintenance Schedule
| Filter Type | Maintenance Frequency | Notes |
|---|---|---|
| pre-filter | Clean every 2 days | replace every 1-2 months |
| medium filter | Check weekly | replace every 3 months |
| Sub-HEPA | Annual replacement | replace if contaminated |
| HEPA filter | Annual check | replace if resistance >160Pa or after 3 years |
Zone Definitions
Semi-Contaminated Area
Potentially contaminated zone. Transition area.
Includes: Nurse stations, treatment rooms, equipment processing
Contaminated Area
Patient treatment zone. Contains infectious materials.
Includes: Patient rooms, waste areas, admission rooms
Buffer Room
A transitional space with doors on both sides between zones for staff preparation and decontamination.
This comprehensive guide to negative pressure isolation wards covers essential design requirements, operational protocols, and safety measures for effective infection control in healthcare settings.
Based on international standards and best practices for airborne infection isolation
faq(Frequently Asked Questions)
What is meant by the term negative-pressure isolation room?
A negative-pressure isolation room operates at lower air pressure than the adjacent areas, making the air flow inwards into the room instead of moving out of the room. The exhaust air is either discharged safely outside of the room or is treated appropriately to eliminate the infective particles that are carried in the air.
In which case patients should be put in isolation rooms?
These rooms are intended for patients who are diagnosed or suspected to be suffering from diseases spread through the air. The decision about putting patients in isolation depends on the current public health regulations, the facility’s risk management assessment, and the recommendations of preventive medicine specialists.
What should be the pressure difference between the isolation room and adjacent areas?
The pressure difference between the isolation room and adjacent rooms depends on state regulations and standards effective in the particular healthcare facility. Sometimes the pressure difference is accepted to be 2.5 Pa, however, it can be different in accordance with local regulations. The pressure must be indicated during the whole time of the mode providing the information on the pressure to be presumptive upon performing.
What type of personal protective equipment should the staff wear?
The used protective equipment is determined by the risk of infection spread, which should be determined to make it clear to the physician the type of wearing protective equipment. Staff members must be aware of how to properly put on and take off the equipment to avoid infecting themselves. The staff must use the protective equipment in accordance with the rules stated in professional literature.
How to perform monitoring of ventilation?
The monitoring of ventilation requires monitoring the pressure state in the room, direction of airflow, ventilation speed, alarm signaling, and the condition of the exhaust ventilation system. For this purpose, the medical facility uses visual and Electronic monitoring equipment as well as smoke visualization technologies and devices selected in accordance with the specifications of the equipment.
What approach should be used for cleaning a negative-pressure isolation room?
The cleaning of the surfaces of high risk of contamination should be performed by qualified staff members using disinfectants approved by the medical authorities for the use against the suspected pathogen. All cleaning procedures should be performed in accordance with the specifications of the disinfectants used in the process. The cleaning of the tools must be performed before putting them into use again.